The ACA Subsidy Cliff Is Back: What to Check Before You Pick a 2027 Plan
Enhanced ACA credits expired after 2025. The 2027 income lines and rates are final, benchmark premiums rose 13% — what changed, and four checks to run.
Open enrollment for 2027 ACA Marketplace coverage opened on November 1, 2026 and runs through January 15, 2027 — with December 15, 2026 the deadline to have coverage in place on January 1 — and for anyone whose household income sits anywhere near four times the federal poverty level, this is the second enrollment season under rules that many enrollees have not internalized yet. The temporary “enhanced” premium tax credits that ran from 2021 through 2025 expired on December 31, 2025, and the subsidy structure reverted to the original ACA design. If your picture of ACA subsidies still includes “8.5% of income no matter what,” that picture is out of date.
This year the arithmetic can finally be done on published numbers rather than estimates. The IRS issued the 2027 applicable percentages in July 2026, and the poverty guidelines that govern 2027 coverage were published in January.
What the cliff actually is
The original ACA premium tax credit is available to households earning between 100% and 400% of the federal poverty level (FPL), with the required premium contribution rising stepwise as income rises. Above 400% FPL, the credit is zero — a hard cutoff, not a phase out. Earn one dollar over the line and you lose the entire credit, not a slice of it.
In dollars, using the 2026 poverty guidelines that govern the 2027 plan year (48 contiguous states and DC), the line sits at:
- $63,840 for a household of one
- $86,560 for a household of two
- $109,280 for a household of three
- $132,000 for a household of four
Alaska and Hawaii use higher figures. The single-person baseline is $15,960, and each additional person adds $5,680 to that baseline — which, at the 400% line, means $22,720 per additional person. So for a household larger than four, add $22,720 rather than assuming the four-person number stretches.
(One technical note, because it is the step people get wrong. The rule at 26 C.F.R. § 1.36B-1(h) applies the poverty guidelines in effect on the first day of the open enrollment period for the coverage year — here, the 2026 guidelines in effect on November 1, 2026 — not the guidelines published during the coverage year itself. Planning on the 2027 numbers, if you happen to have seen them, puts your estimate on the wrong line.)
Crossing the cliff does not lock you out of coverage: you can still buy any Marketplace plan at full price. A household whose cheapest available plan would cost more than a separate, lower threshold — 8.50% of household income for 2027 — may qualify for an affordability exemption that permits purchasing a lower-premium Catastrophic plan. That 8.50% is the required contribution percentage HHS indexes each year under 26 U.S.C. § 5000A(e)(1), and it is not the 10.22% figure further down this page: 10.22% is the top of the sliding scale for what you contribute toward a benchmark plan, and it also sets whether an employer offer blocks a credit, while 8.50% is the test for the Catastrophic exemption. The two are routinely mixed up, and mixing them makes the Catastrophic route look closed to households that actually qualify. The exemption is conditional, not automatic — and it varies by state, because some states run their own exchanges and some add state-funded subsidies of their own. The subsidy itself is gone on the federal platform.
One distinction worth keeping straight, because the two are often merged in coverage of the 2027 plan year: the affordability exemption above is not the same as the income-based hardship expansion that would have opened Catastrophic plans to anyone ineligible for a premium tax credit because their income fell below 100% or above 250% of the poverty level. A federal court stayed that income-based route on July 16, 2026, and it is not in effect for 2027. The affordability test, not income alone, is what governs. We walk through the stayed provisions and what remains in The 2027 Marketplace runs on a court-modified rule.
The Congressional Budget Office has estimated that letting the enhanced credits expire would substantially reduce the number of people covered by subsidized exchange plans, and industry analyses have put those newly ineligible in the millions.
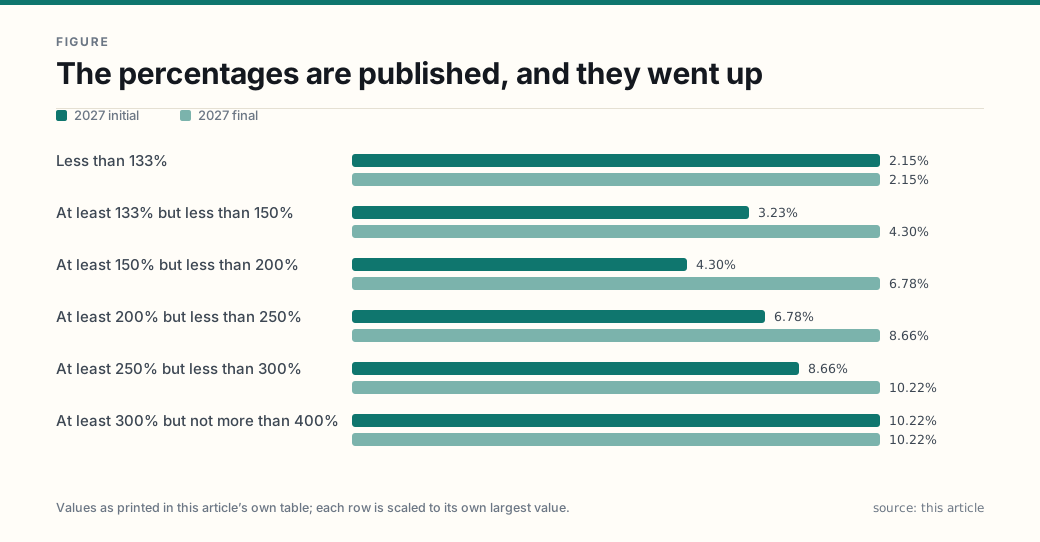
The percentages are published, and they went up
The applicable percentage is the share of household income you are expected to contribute toward a benchmark plan. The IRS publishes it annually; Rev. Proc. 2026-26 sets it for plan years beginning in 2027:
| Household income as % of FPL | 2027 initial | 2027 final |
|---|---|---|
| Less than 133% | 2.15% | 2.15% |
| At least 133% but less than 150% | 3.23% | 4.30% |
| At least 150% but less than 200% | 4.30% | 6.78% |
| At least 200% but less than 250% | 6.78% | 8.66% |
| At least 250% but less than 300% | 8.66% | 10.22% |
| At least 300% but not more than 400% | 10.22% | 10.22% |
The top of the scale moved from 9.96% for 2026 coverage to 10.22% — the first time the figure has crossed 10%. If you are near the cliff, that is about a quarter-point more of your income going to the benchmark premium before any credit is calculated. Nothing dramatic on its own; meaningful in combination with what premiums themselves did.
What CMS published the day before the window opened
On October 30, 2026 CMS released its Plan Year 2027 Marketplace Plans and Prices fact sheet — one day before enrollment opens, and worth reading for what it asserts and for what it does not.
As CMS states it:
- More than 75% of Americans who buy through HealthCare.gov “will continue to have access to premiums at or below $50 in 2027.”
- People eligible for tax credits will have “access to a plan with nearly 90% of the lowest-cost premium paid for by the federal government, compared to 85% in 2020.”
- On average, Americans have access to 100 different plans and five to six insurance companies.
- The average premium of the lowest-cost catastrophic plan is “nearly 10% cheaper than the next lowest-cost plan at other coverage levels.”
- Eligible enrollees have access to 35 HSA-eligible plans on average — a consequence of the 2025 tax law treating bronze and catastrophic Marketplace plans as high-deductible health plans. Read the first figure with its verb. “Access to” a premium at or below $50 is not the same as paying at or below $50. CMS does not define the metric; most plausibly it describes the lowest-cost plan available to a subsidized enrollee in a market, as a monthly premium — not the median bill and not yours. Your premium depends on income, household size, age, county and the plan you choose, so anyone comparing that sentence to their own quote should expect the two to differ, and should trust the quote.
The same care applies to what the fact sheet does not say. It publishes no average 2027 premium and no comparison with 2026 — an independent measurement of both exists, and it is the next section — and its text does not mention the 400% FPL line, the expired enhanced credits, or the reconciliation rules anywhere. That is not a contradiction of anything above — it is simply not addressed. For a household near the line, the numbers that decide the outcome are still the ones on this page.
One line in it is directly useful for a decision you may be making this week: the comparison between the cheapest catastrophic plan and the next metal level. If your income puts you above the subsidy line and the affordability test is the route you are considering, that gap is the practical measure of what a Catastrophic plan saves you. What is offered at that level is local, though — check your own county’s plan list rather than a national average.
The HSA item is the one change here that is unambiguously good news and easy to miss. If you have an HSA-eligible plan available and you hold an HSA, the account rules are in The HSA as a retirement account — including the 2027 contribution limits and the reason paying Medicare premiums from the account is allowed while Medigap premiums never are.
How much did 2027 premiums actually go up?
The published figure is 13%. KFF’s open-enrollment analysis, issued November 6, 2026 and corrected the same day, measures the finalized 2027 benchmark silver premium — the second-lowest-cost silver plan in each rating area, the figure the premium tax credit is built on — at an average of 13% above 2026 across the 50 states and the District of Columbia. The same analysis puts the two halves of the market far apart:
| Change in the benchmark silver premium | 2025 → 2026 | 2026 → 2027 |
|---|---|---|
| National average, 50 states and DC | +26% | +13% |
| States using the HealthCare.gov platform | +30% | +11% |
| State-run marketplaces | about +17% | +16% |
KFF puts the two-year increase at 42% between 2025 and 2027 on the same average — its own figure, computed from average dollar premiums rather than by multiplying the two percentages above. Insurers proposed a median 15% increase; the finalized national average of 13% came in below that median, though a median request and an average final rate are different statistics and are not strictly comparable.
KFF reports the causes as the insurers give them: a higher-than-usual increase in the underlying cost of care — which it notes is not unique to the Marketplace, since some employer plans saw steep increases too — plus a risk-pool effect. Insurers estimated that pool changes added about four percentage points to 2026 premiums and expect a similar additional effect in 2027, after the enhanced credits expired. That is the attribution insurers gave KFF, repeated here as attribution rather than as a finding.
Two numbers, two different questions
13% and CMS’s “more than 75% will have access to premiums at or below $50” are not in conflict, because they measure different things. 13% is the change in the benchmark premium before any credit; the $50 line describes the lowest-cost plan available to a subsidized enrollee in a market. A market can post a sharp benchmark increase and still have cheap entry-level plans, and in 2027 it does. Which of the two describes your situation depends entirely on where your income sits — which is the argument of this page.
What a 13% benchmark increase does to a subsidized household
The credit is not a fixed dollar amount. It is the benchmark premium minus a required contribution set as a percentage of household income, the structure at 26 U.S.C. § 36B(b). Two consequences follow, and they are ours from the statute rather than KFF’s:
- In the benchmark plan, the increase is absorbed rather than passed through — where a credit is payable at all. With income and household size unchanged, the credit grows to cover the difference: your premium stays at the applicable percentage of your income, and what changes is the percentage itself. At the top of the subsidy range that is 10.22% for 2027 against 9.96% for 2026 — about 2.6% more in dollars (10.22 ÷ 9.96 = 1.026), not 13%. The exception is a rating area where the benchmark premium is already below your required contribution: no credit is payable there, so you pay the plan’s actual price and the increase lands on you in full even below 400% FPL.
- Above 400% FPL, none of it is absorbed. There is no credit to grow, so the full increase applies. 13% is a national average; your renewal notice carries the figure for your county, your age band and your plan.
The practical reading for a household near the line: the cliff, not the average, is what changes your year. At 420% FPL you pay the entire increase; at 380% FPL you pay roughly the applicable-percentage change. That asymmetry is why this page leads with the dollar line rather than the rate.
What happened to enrollment, for context
KFF also records what the first year without the enhanced credits did to the market — the backdrop to any 2027 decision:
- Marketplace plan selections during the 2026 open enrollment period fell by 1.2 million from 2025.
- Effectuated enrollment — people who paid and stayed enrolled — was 19.2 million in February 2026, down 12%, or 2.6 million people.
- The wider individual market, which includes off-exchange plans, fell 18% between 2025 and June 2026, from 25.2 million to 20.5 million.
- KFF reports that the Congressional Budget Office now projects Marketplace enrollment falling from a 2025 peak of 22.4 million to 13.1 million in 2027.
None of that is a reason to skip coverage. It is a reason not to assume the plan you held last year will be offered, priced or networked the same way — and a reason to confirm your own county’s numbers in the plan comparison tool at HealthCare.gov or your state exchange, not to plan around a national average.
Four changes that ride along with the reversion
The cliff gets the headlines, but the reversion changed enrollment mechanics in ways that matter just as much this November:
- Contribution percentages went up. As above: the required contribution at each income level returned to the original ACA schedule, indexed for inflation, and for 2027 it is higher at the top rungs than under the enhanced credits.
- Repayment caps are gone. If you take the credit in advance and your actual income ends the year higher than you estimated, you reconcile the difference on your tax return. For 2021 through 2025 the enhanced credits limited how much a household had to repay; with the enhancement expired, that limit no longer applies for 2026 and later tax years. Underestimating income near the cliff now repays the full excess credit.
- Re-enrollment is no longer automatic with the credit attached. Under CMS’s 2025 Marketplace Integrity rule, the federal platform stopped simply rolling coverage and subsidy over year after year: enrollees who do not verify their information face a monthly surcharge during the transition, and skipping verification altogether puts the advance credit at risk. Practically, treat re-enrollment as an annual task — confirm your information, check your plan, and re-attach the credit deliberately.
- The under-150% FPL year-round window ended. Very-low-income households lost the monthly special enrollment period and now enroll during the standard window or after a qualifying life event. This mechanic applies on the federal platform; state-run marketplaces set their own rules and deadlines, so confirm on HealthCare.gov or your state’s marketplace before you plan around a date.
One protection survived, but the dollar figures stepped up with everything else. Cost-sharing reductions (lower deductibles and out-of-pocket maximums) still apply to Silver plan enrollees earning 100–250% FPL. For 2027 the reduced out-of-pocket maximum is $4,000 for enrollees at 100–150% and at 150–200% FPL, and $9,600 for 200–250% FPL — against a standard ACA ceiling of $12,000 for self-only coverage. If your income is in that band, a Silver plan is usually the right place to start looking, and the gap between Silver and Bronze is larger than the premium difference alone suggests.
A correction to what this page said before. An earlier version of this article said the federal open-enrollment window “now closes at the end of December rather than running to mid-January.” That came from the 2025 Marketplace Integrity rule, which would have closed the federal window in mid-December from the 2027 plan year onward. The provision was vacated by a federal court in June 2026, and CMS later confirmed that HealthCare.gov states would keep the traditional window: November 1, 2026 through January 15, 2027, with December 15, 2026 the deadline for coverage starting January 1. HHS has appealed, so the schedule for the 2028 season is not settled — but the 2027 dates are the ones to plan around. State-run marketplaces set their own deadlines, and they do not all match the federal one — check your state’s exchange rather than assuming the HealthCare.gov dates apply to you.
The legislative status is live — do not plan around a bill
A bill to restore the enhanced credits passed the House earlier in this Congress with some Republican support and stalled in the Senate, so it did not become law.
The November 3, 2026 midterm elections changed who will control the next Congress, and that has produced a specific promise with a specific calendar attached. The Associated Press reported on November 7, 2026 that House Democratic leaders expect early votes on restoring the enhanced premium tax credit once the new Congress is sworn in on January 3, 2027, and that Hakeem Jeffries, in line to become speaker, put it among his first priorities: “We’re going to get out of the gate fast.” AP reports that House Democrats will hold more than 250 of the 435 seats when that Congress convenes.
Read that against the enrollment calendar and the arithmetic is unforgiving. January 3, 2027 is nineteen days after December 15, 2026 — the last day to enroll or change plans for coverage that starts on January 1. No vote the incoming majority has promised can arrive before the deadline that decides what you pay in January.
Three further facts belong beside that one, because each narrows what a vote could do for you:
- A 60-vote Senate threshold still governs, and AP reports that a potential presidential veto also stands in the way — the President posted a red hat reading “VETO” on election night. Passage in the House is not in doubt; enactment is a different question.
- A vote is not a payment. Whether a restored credit would apply to January premiums, to the whole of 2027, or only forward is a separate question from whether it passes, and it is answered by the enrolled text — not by a leadership statement in November.
- The disagreement has not gone away. AP reports Senate Democratic leader Chuck Schumer as saying he is getting initial signs of Republican support “on certain issues, not on every issue,” while the President’s veto post is the opposing signal. A restored credit would need both a Senate majority and a signature.
None of that tells you what will happen — only what to do with the question. Plan with the law as it stands today, verify the current status on congress.gov and HealthCare.gov when you enroll, and treat any “subsidies are coming back” claim from an insurance salesperson as a closing tactic, not a fact. If a restoration is enacted later in 2027, check its effective date before assuming it changes a premium you have already paid, and update your Marketplace application rather than waiting for the reconciliation on your return.
One scam warning that belongs with this topic
Subsidy season is when “free money” offers multiply. Two rules cover almost all of it: no one can sell you eligibility, and the Marketplace never asks for a fee to compute or release a premium tax credit. Enrollment help is free at HealthCare.gov and at state exchanges. Anyone charging a fee to “unlock your subsidy,” offering a “special enrollment window” by cold call, or asking for your Login.gov password or a one-time code is not helping you enroll — that is fraud, and it is worth naming as such. If a pitch creates urgency because the money expires soon, the urgency is the tell.
Four checks to run before you enroll
- Locate yourself against the line. Eligibility uses your projected household MAGI (modified adjusted gross income) for the coverage year — roughly adjusted gross income plus tax-exempt interest, untaxed Social Security benefits and excluded foreign income. Project 2027, not 2026. Know your household size’s dollar line: $63,840 for one, and $22,720 more for each additional person up to the four-person figure of $132,000. (The poverty guideline itself rises $5,680 per person; at the 400% line that becomes 4 × $5,680.)
- If you are near the line, manage MAGI legally and early. Pre-tax contributions — traditional 401(k), IRA, HSA — reduce MAGI. For a household hovering near 400% FPL, a retirement contribution made by December 31 can be the difference between a subsidized plan and full price. This is a decision to make in December, not at tax time.
- If your income is variable, estimate conservatively. With repayment caps gone, an optimistic income estimate near the cliff is a tax bill waiting to happen. Estimate high rather than low if you are unsure, and report income changes to the Marketplace during the year instead of waiting to reconcile.
- Re-enroll actively and check plan fit, not just price. Verify your information, run your actual numbers through the Marketplace, and if your income is 100–250% FPL, price Silver plans for the cost-sharing reduction. Premium is only part of the bill — the deductible structure is the rest, and the out-of-pocket ceiling itself moved up $1,400 for self-only coverage this year.
The mechanics of the Marketplace itself are in ACA Marketplace Basics, the four cost numbers that decide what you actually pay are in Premium, Deductible, Copay, Out-of-Pocket Max, and the refund checks that spawned a wave of “release your payment” scams this fall are covered in The $500 Obamacare Refund.
Bottom line
The cliff is the law until Congress changes it, and it turns a modest income difference into a total subsidy loss. Know your household’s dollar line, project your 2027 MAGI honestly, lean conservative if your income varies, and re-enroll actively — the window is open now and closes January 15, 2027, with December 15, 2026 the deadline for coverage that starts on January 1. The worst outcome is not paying full price on purpose — it is discovering the cliff on your tax return.
This article is general information about federal Marketplace rules, not advice about your specific tax situation or plan choice. Eligibility figures depend on household size, state and year — confirm current numbers at HealthCare.gov.
Frequently asked questions
- What income triggers the ACA subsidy cliff for 2027 coverage?
- The enhanced credits expired after 2025, so the original rule applies again: households above 400% of the federal poverty line generally cannot qualify for a premium tax credit. Using the 2026 poverty guidelines that govern 2027 coverage, that line sits at about $63,840 for a household of one and $132,000 for a household of four in the 48 contiguous states and DC.
- CMS says most enrollees will have access to premiums at or below $50 in 2027. Is that what I will pay?
- Not necessarily, and the wording matters. CMS's October 30 fact sheet says more than 75% of people buying through HealthCare.gov will have access to premiums at or below $50 — CMS does not define the metric, but it most plausibly describes the lowest-cost plan available to a subsidized enrollee in a market, not the median bill and not yours. Your own premium depends on your income, household size, age, county and the plan you pick, so run your numbers rather than reading the headline as a forecast.
- Can I still buy Marketplace coverage if I am over the line?
- Yes — the cliff ends the subsidy, not the access. Anyone can buy a Marketplace plan at full price. A household whose cheapest available plan would cost more than the affordability threshold may qualify for an affordability exemption that permits a Catastrophic plan. That threshold is 8.50% of household income for 2027 — the required contribution percentage HHS indexes under 26 U.S.C. § 5000A(e)(1), which is a different and lower number than the 10.22% applicable percentage. It is also a separate route from the income-based hardship expansion, which a federal court stayed in July 2026 and which is not in effect for 2027. Run the numbers before you enroll rather than assuming you are locked out.
- What happens if my income estimate turns out to be wrong?
- If you end up earning more than you projected, excess premium tax credit is reconciled on your tax return — and with the repayment caps gone, the amount owed is no longer limited. If you earn less, you may qualify for more subsidy. Update your Marketplace application when your income changes rather than waiting for tax season.
- Benchmark premiums rose 13% for 2027. Will my subsidized premium rise that much?
- Usually not, if your income stays in the same range and you keep the benchmark plan. The premium tax credit is the benchmark premium minus a set share of your income, so wherever a credit is payable the increase is absorbed by a larger credit and your premium stays at that share of income. What rises for you is your share: at the top of the subsidy range the required contribution is 10.22% of income for 2027 instead of 9.96% for 2026, which is about 2.6% more in dollars. Above 400% of the federal poverty level there is no credit, so the full increase — 13% on average nationally, more or less in your county — lands on you. The same is true in a rating area whose benchmark premium already sits below your required contribution: no credit is payable, so you pay the plan's price.
- Will Congress restore the enhanced subsidies in time for January 1, 2027?
- Not on any schedule now public. The incoming House majority says restoring the credit will be among its first votes, but the new Congress is sworn in on January 3, 2027 — nineteen days after the December 15 deadline for coverage starting January 1 — and a 60-vote Senate threshold plus a veto threat stand between a vote and a signed law. Whether a restored credit would apply retroactively is a separate question with no published answer. Enroll by December 15 under current law and treat any later restoration as a possible amendment, not a plan.
Sources
Each source is a primary or official reference, checked before publication. Links open the original.
- IRS Revenue Procedure 2026-26 — applicable percentage table and required contribution percentage for plan years beginning in 2027 (irs.gov/pub/irs-drop/rp-26-26.pdf)
- KFF, '9 Things to Watch for the 2027 ACA Open Enrollment Period' (published November 6, 2026; Table 1 corrected the same day) — the 13% average increase in finalized 2027 benchmark silver premiums, the 11% HealthCare.gov versus 16% state-based marketplace split, the 26% (2025–2026) and 42% (2025–2027) comparison figures, the 15% median insurer request, the roughly four-point risk-pool effect, and the enrollment figures (kff.org/affordable-care-act/9-things-to-watch-for-the-2027-aca-open-enrollment-period/)
- HHS, 'Annual Update of the HHS Poverty Guidelines,' 91 Fed. Reg. 1797 (January 15, 2026) — the 2026 guidelines that govern 2027 coverage under 26 C.F.R. § 1.36B-1(h) (govinfo.gov)
- CMS, 'Plan Year 2027 Marketplace Plans and Prices Fact Sheet' (October 30, 2026) — the 2027 open enrollment dates, the 75%-at-or-below-$50 access figure, the 90%-versus-85% federal share of the lowest-cost premium, the 100-plan and five-to-six-insurer averages, the catastrophic-plan price comparison and the 35 HSA-eligible plans average (cms.gov/newsroom/fact-sheets/plan-year-2027-marketplace-plans-prices-fact-sheet-0)
- CMS, 'Premium Adjustment Percentage, Maximum Annual Limitation on Cost Sharing, Reduced Maximum Annual Limitation on Cost Sharing, and Required Contribution Percentage for the 2027 Benefit Year' (January 29, 2026) — the $12,000 self-only out-of-pocket maximum, the reduced cost-sharing limits, and the 8.50% required contribution percentage under 26 U.S.C. § 5000A that governs the Catastrophic affordability exemption at 45 C.F.R. § 155.305(h) (cms.gov/files/document/2027-papi-parameters-guidance-2026-01-29.pdf)
- The Associated Press, 'House Democrats will start their majority focused on boosting healthcare and ending the Iran war' (November 7, 2026; syndicated copy at aol.com) — the January 3, 2027 swearing-in, the early-vote commitment on the enhanced premium tax credit, the previous House passage with some Republican support and the Senate stall, Jeffries's 'get out of the gate fast' quote, the more-than-250 House seats, the 60-vote Senate threshold, the veto threat behind the election-night 'VETO' post, and Schumer's 'initial signs … on certain issues' quote
- Congressional Research Service, R48290, 'Enhanced Premium Tax Credit and 2026 Exchange Premiums: Frequently Asked Questions' (updated December 10, 2025) — congress.gov
- American Rescue Plan Act (P.L. 117-2) and Inflation Reduction Act (P.L. 117-169) — enhanced PTC in effect for tax years 2021–2025
- CMS 2025 Marketplace Integrity and Affordability Final Rule, 90 Fed. Reg. 27074 (June 25, 2025) — end of automatic re-enrollment with credit and of the under-150% FPL year-round window
- HealthCare.gov, 'When can you get health insurance?' (healthcare.gov/quick-guide/dates-and-deadlines/) — the 2027-cycle dates: open enrollment November 1, 2026 through January 15, 2027; December 15, 2026 as the last day to enroll or change plans for coverage starting January 1; February 1 as the start date for enrollments made December 16 through January 15; and the eligibility-verification pages. Login.gov is the account system used to sign in to federal benefits applications
- City of Columbus et al. v. Kennedy, No. 1:26-cv-02215 (D. Md.), order entered July 16, 2026 — the stay of the 2027 payment rule's income-based Catastrophic-plan hardship expansion, which is why the affordability test (not income alone) governs for 2027